
Course Content
OSCE Station 1 — Sore Throat: Focused History, Examination and Initial Management
KMU clinical activities: History Taking • Examination of Sore Throat Patient • Conservative Management of Sore Throat Learning Objectives The student should be able to: • Obtain a focused history from a patient presenting with sore throat. • Perform relevant general physical examination. • Perform systematic local examination of the throat. • Perform relevant systemic examination. • Identify important clinical findings in a patient with sore throat. • Discuss a conservative management plan for acute follicular tonsillitis.
0/1
OSCE Station 2 — Oral Cavity, Oropharynx, Nasopharynx and Hypopharynx Examination
KMU clinical activities: Nasopharyngeal Examination • Oral Cavity and Oropharynx Examination • Hypopharyngeal Examination • Oral/Oropharyngeal Mass Palpation • Biopsy from Oral Ulcer Learning Objectives The student should be able to: • Examine the oral cavity systematically. • Examine the oropharynx systematically. • Perform mirror examination of the nasopharynx. • Perform indirect hypopharyngoscopy using a mirror. • Demonstrate the method of palpating a mass in the oral cavity or oropharynx. • Describe the basic steps involved in assisting with biopsy of a tongue/oral ulcer. • Identify important abnormal findings during examination of the upper aerodigestive tract.
0/1
OSCE Station 3 — Tonsillectomy: Consent, Instruments and Theatre Skills
KMU clinical activities: Mouth Gag and Tonsillectomy Instruments • Tonsillar Surgery • Tonsillectomy Consent • Scrubbing Technique Learning Objectives The student should be able to: • Identify and assemble the mouth gag used for tonsillectomy. • Identify common tonsillectomy instruments. • State the use of each instrument. • Recognize the important procedural steps of tonsillectomy. • Obtain appropriate pre-operative informed consent for tonsillectomy. • Explain the procedure, expected benefits and relevant patient information during consent. • Demonstrate correct surgical hand-scrubbing technique. • Use an appropriate scrubbing solution, sequence and duration.
0/1
OSCE Station 4 — Dysphagia: Rigid Endoscopy System and Oesophagoscopy
KMU clinical activities: Rigid Endoscopy System • Oesophagoscopy Learning Objectives The student should be able to: • Identify the main instruments and equipment used in a rigid endoscopy system. • Describe the basic types and purposes of rigid endoscopy. • Identify a rigid oesophagoscope and associated equipment. • Describe the basic steps of rigid oesophagoscopy. • Explain its use in patients presenting with dysphagia or pharyngeal growth. • Recognize the important safety principles associated with rigid oesophagoscopy.
0/1
OSCE Station 5 — Hoarseness and Stridor: Focused History and Clinical Examination
KMU clinical activities: History Taking • Examination in Hoarseness and Stridor • Examination of Neck Learning Objectives The student should be able to: • Obtain a focused history of hoarseness. • Obtain a focused history of stridor. • Perform relevant general physical examination. • Perform appropriate local ENT examination. • Perform relevant systemic examination. • Perform a systematic examination of the neck. • Identify clinical features that require further laryngeal assessment.
0/1
OSCE Station 6 — Laryngeal Examination: Indirect, Video and Rigid Laryngoscopy
KMU clinical activities: Indirect Laryngoscopy • Investigations of Laryngeal Disease • Video Laryngoscopy • Rigid Laryngoscopy • Biopsy from Laryngeal Growth Learning Objectives The student should be able to: • Perform indirect mirror examination of the laryngopharynx. • Demonstrate correct patient and examiner positioning for indirect laryngoscopy. • Identify important structures seen during laryngeal examination. • Select appropriate investigations for laryngeal disease. • Complete or explain an appropriate investigation requisition. • Recognize the role of video laryngoscopy in a patient with hoarseness. • Identify important findings on a laryngoscopic image or video. • Identify the instruments used in rigid laryngoscopy under general anaesthesia. • Describe the basic procedure of rigid laryngoscopy. • Describe the basic steps involved in obtaining a biopsy from a laryngeal growth.
0/1
OSCE Station 7 — Voice Disorders and Laryngeal Patient Counselling
KMU clinical activities: Conservative Management of Hoarseness • Voice-Rest Counselling • Bilateral Abductor Vocal-Cord Paralysis Counselling • Laryngectomy Consent Learning Objectives The student should be able to: • Discuss conservative management of hoarseness due to voice abuse. • Counsel a patient regarding appropriate voice rest. • Explain practical measures for reducing further vocal strain. • Counsel a patient with bilateral abductor vocal-cord paralysis following thyroidectomy. • Discuss the relevant management principles for bilateral vocal-cord paralysis. • Communicate clearly and empathetically with a patient facing major laryngeal treatment. • Obtain appropriate informed consent for total laryngectomy.
0/1
OSCE Station 8 — Tracheostomy and Emergency Airway Procedure
KMU clinical activity: Tracheostomy Learning Objectives The student should be able to: • Identify the important anatomical landmarks relevant to tracheostomy. • Identify essential instruments and equipment used for tracheostomy. • Demonstrate or describe the sequence of the tracheostomy procedure. • Explain appropriate positioning of the patient. • Describe the principle of establishing a surgical airway. • Recognize important immediate precautions during and after tracheostomy.
0/1
OSCE Station 9 — Ear Examination: History, Otoscopy and Examination Under Microscope
KMU clinical activities: Ear History Taking • Local Examination • Otoscopy • Examination Under Microscope Learning Objectives The student should be able to: • Obtain a focused history from a patient with ear discharge, deafness or dizziness. • Perform systematic local examination of the ear. • Demonstrate correct handling of an otoscope. • Perform an otoscopic examination safely. • Identify the external auditory canal and tympanic membrane. • Recognize common abnormal otoscopic findings. • Explain the basic role of examination under microscope (EUM). • Describe how the student may assist during EUM.
0/1
OSCE Station 10 — Hearing and Balance Assessment: Tuning Forks, Vestibular Tests and Audiology
KMU clinical activities: Tuning-Fork Tests • Balance Testing • Ear Investigations • Audiogram and Impedance Interpretation Learning Objectives The student should be able to: • Perform appropriate tuning-fork tests. • Demonstrate the correct technique of the Rinne test. • Demonstrate the correct technique of the Weber test. • Interpret common tuning-fork test patterns. • Perform appropriate clinical tests of balance. • Differentiate clinical findings suggesting peripheral versus central balance dysfunction. • Select appropriate investigations for common ear diseases. • Complete an appropriate investigation requisition. • Interpret a basic pure-tone audiogram. • Interpret basic impedance/tympanometry findings.
0/1
OSCE Station 11 — Nasal Obstruction: History, Nose and PNS Examination and Adenoid Assessment
KMU clinical activities: History Taking • Local Examination • Nasal Patency and Adenoid Facies Learning Objectives The student should be able to: • Obtain a focused history from a patient with nasal obstruction. • Perform systematic external examination of the nose. • Perform relevant clinical examination of the paranasal sinus region. • Assess nasal patency. • Compare airflow through both nasal cavities. • Recognize clinical features of adenoid facies. • Examine nasal patency in a patient with suspected enlarged adenoids.
0/1
OSCE Station 12 — Rhinoscopy and Nasal Procedures: Probe Test, Nasendoscopy and Nasal Swab
KMU clinical activities: Anterior Rhinoscopy • Posterior Rhinoscopy • Probe Test • Nasendoscopy • Pus Culture/Sensitivity Learning Objectives The student should be able to: • Perform anterior rhinoscopy systematically. • Demonstrate the technique of posterior rhinoscopy using a mirror. • Identify important structures visualized during rhinoscopy. • Perform or describe the probe test. • Explain the basic principles of nasendoscopy. • Describe how to assist during nasendoscopy. • Demonstrate the correct method of obtaining a nasal swab. • Explain appropriate specimen handling for culture and sensitivity.
0/1
OSCE Station 13 — Nose and Paranasal Sinus Imaging and Investigations
KMU clinical activities: X-Ray Nasopharynx/PNS • CT Nose and Nasopharynx • Investigation Requisition Learning Objectives The student should be able to: • Interpret a basic X-ray of the nasopharynx/PNS. • Identify an enlarged soft-tissue shadow associated with enlarged adenoids. • Approach a CT scan of the nose and nasopharynx systematically. • Recognize CT findings associated with juvenile nasopharyngeal angiofibroma. • Identify and explain the bowing sign. • Select appropriate investigations for diseases of the nose and paranasal sinuses. • Complete an appropriate investigation requisition form.
0/1
OSCE Station 14 — Adenoid and Nasopharyngeal Procedures
KMU clinical activities: Adenoid Surgery • Nasopharyngeal Biopsy Learning Objectives The student should be able to: • Identify the basic setup used for adenoid surgery. • Describe the major procedural steps of adenoidectomy as observed in theatre. • Identify important instruments used during adenoid surgery. • Describe the basic principles of obtaining a nasopharyngeal biopsy. • Identify the purpose of nasopharyngeal biopsy. • Recognize key safety considerations during procedures involving the nasopharynx.
0/1
OSCE Station 15 — Neck Examination: Lymph Nodes, Neck Lump, Thyroid and Parotid
KMU clinical activities: Examination of Neck • Examination of Neck Nodes • Neck Lump Examination • Thyroid Examination • Parotid Examination Learning Objectives The student should be able to: • Perform a systematic examination of the neck. • Examine the major groups of cervical lymph nodes. • Describe the location of the major cervical nodal groups. • Perform systematic examination of a neck lump. • Assess the site, size, surface, consistency, mobility and associated features of a neck swelling. • Perform examination of the thyroid gland. • Assess thyroid enlargement anatomically. • Perform relevant functional assessment of the thyroid as required by the station. • Perform systematic examination of a parotid swelling. • Identify clinical features that help characterize a salivary-gland swelling.
0/1
OSCE Station 16 — Pharyngeal and Peritonsillar Abscess: Drainage and Instruments
KMU clinical activities: Surgery on Pharyngeal Abscess • Pharyngeal Abscess Surgery-Related Instruments Learning Objectives The student should be able to: • Recognize the basic principles of surgical management of a pharyngeal abscess. • Describe the technique of drainage of a peritonsillar abscess. • Identify important instruments used for drainage of a pharyngeal or peritonsillar abscess. • State the use of each relevant instrument. • Describe appropriate patient positioning and preparation for drainage. • Recognize important precautions associated with abscess drainage in the upper airway.
0/1
AIM OSPE/OSCE Lab — ENT Module | 4th Year MBBS

AIM OSCE / OSPE • MBBS

Station 16 — Pharyngeal and Peritonsillar Abscess: Drainage and Instruments

4th Year • Rapid Revision • Practical Skills • Viva

🎯 Candidate Task

Describe the preparation and basic technique for drainage of a peritonsillar abscess and identify the important instruments used. State the use of each instrument and the major safety precautions during drainage of an upper-airway abscess.

⚡ Model Station Answer

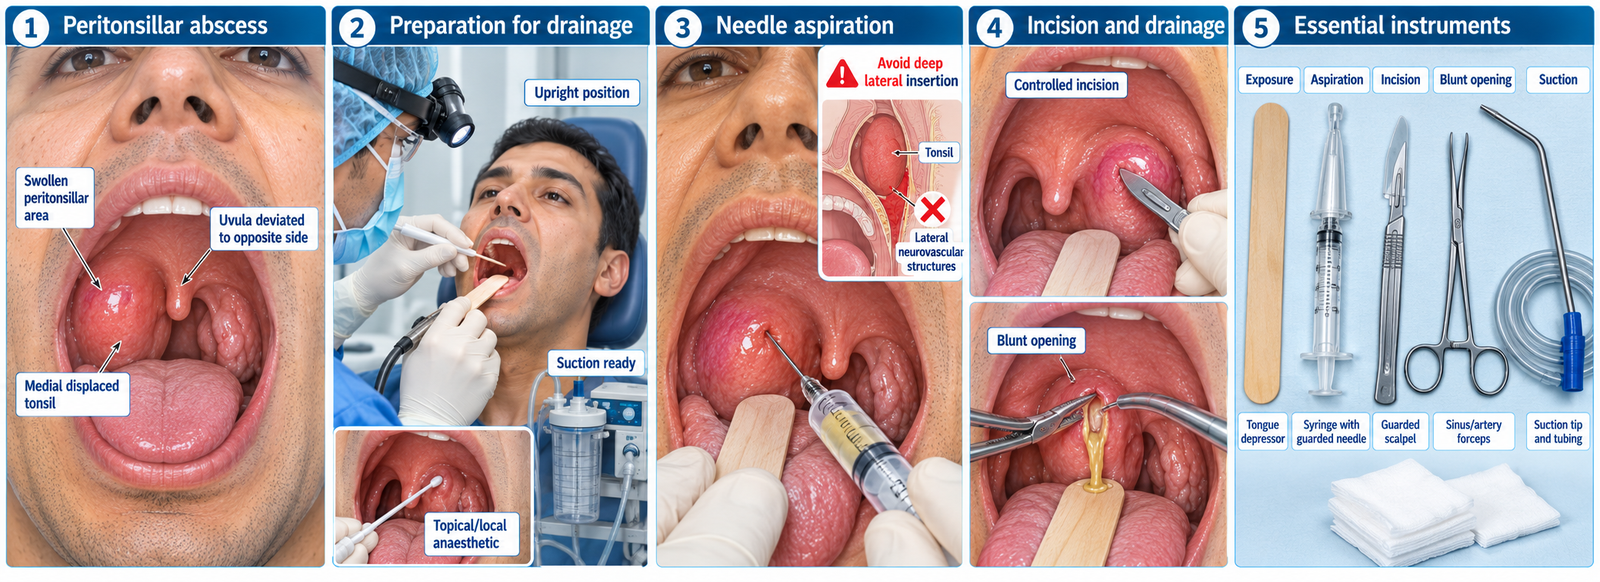
Preparation: I would assess the airway, position the patient sitting upright, ensure good illumination and suction, and use appropriate topical and local anaesthesia.

Drainage: The abscess is localized at the peritonsillar swelling and drained by needle aspiration or a controlled incision followed by gentle opening of the cavity and suction of pus.

Instruments: Important equipment includes a tongue depressor, suction, guarded needle or scalpel and sinus/artery forceps.

Safety: Airway compromise and haemorrhage are major concerns; instrumentation should remain controlled and superficial, with readiness for suction and escalation if complications occur.

🔎 How to Perform / Approach

  1. Step 1 — Assess and prepare:
    Confirm the patient, explain the procedure and assess for airway compromise. Ensure appropriate monitoring, illumination, suction and emergency airway support are available.
  2. Step 2 — Position correctly:
    Seat the conscious patient upright with the head supported and slightly forward so secretions or pus can drain anteriorly rather than toward the airway.
  3. Step 3 — Expose the oropharynx:
    Use a tongue depressor and good illumination to identify the unilateral peritonsillar swelling, displaced tonsil and surrounding landmarks. Apply topical and local anaesthesia as appropriate.
  4. Step 4 — Drain the collection:
    Drainage may be performed by controlled needle aspiration or incision at the appropriate point of maximal peritonsillar bulging. If incised, the opening may be gently widened with suitable forceps to allow pus to escape.
  5. Step 5 — Suction and collect:
    Keep suction immediately available to remove pus and secretions and reduce aspiration risk. A specimen may be collected for microbiological testing when clinically required.
  6. Step 6 — Recognize the instruments:
    Identify the tongue depressor for exposure, suction for clearing secretions and pus, needle and syringe for aspiration, guarded scalpel for controlled incision, and sinus or artery forceps for gentle opening of the drained cavity.
  7. Step 7 — Reassess after drainage:
    Check for bleeding, airway difficulty and clinical improvement. Continue observation and escalate urgently if respiratory compromise or significant haemorrhage develops.
Safety warning: Do not perform deep or uncontrolled lateral instrumentation. Major vessels lie posterolateral to the tonsillar region, and airway deterioration, aspiration or haemorrhage must be anticipated.

🖼️ Visual Learning

VISUAL 1

Peritonsillar Abscess Drainage and Essential Instruments


📝 Important Viva Questions

1. What clinical finding commonly suggests a peritonsillar abscess?

Answer: Unilateral peritonsillar and soft-palate swelling with medial displacement of the tonsil and deviation of the uvula away from the affected side is typical.

2. Why should the patient be positioned upright during drainage?

Answer: Upright positioning improves access and helps pus and secretions drain anteriorly, reducing the risk of aspiration.

3. What are the two basic methods used to drain a peritonsillar abscess?

Answer: The collection may be drained by needle aspiration or by incision and drainage.

4. What is the purpose of sinus or artery forceps during incision and drainage?

Answer: They are used for gentle blunt opening of the incision to facilitate drainage of the abscess cavity rather than for deep cutting.

5. What major complications must be anticipated during peritonsillar abscess drainage?

Answer: Important immediate risks are airway compromise, aspiration of pus or blood and haemorrhage from injury to nearby vascular structures.

Scroll to Top
💬 WhatsApp Support